
Monthly GLP-1 Weight Maintenance: The “First of the Month” Method

GLP-1 maintenance is given on the first of each month.
by Dr. Richard Lipman, MD
Internal Medicine and Endocrinology, reviewed and updated on March 8th, 2026.
In the “First of the Month” method for weight maintenance, patients take one GLP-1 injection on the first day of the month and no further injections until the first day of the next month. In my experience over the past 4 years, the majority of patients maintain their weight within a narrow range after this single injection. Weight control may become more difficult during the final 7 days as hunger slowly returns, but the small amount of weight gained during this period is quickly lost after the next month’s injection.
Why Do We Regain Weight after Weight Loss?
After successful weight loss with GLP-1 medications such as semaglutide (Ozempic/Wegovy) or tirzepatide (Mounjaro/Zepbound), the greatest challenge for the weight-loss patient becomes maintaining that weight loss over time. Most people who lose a large amount of weight regain it within 2 to 3 years. The implications of this cycle of weight loss leading to weight gain go beyond just the numbers on the scale; it directly impacts overall health, often leading to the resurgence of chronic conditions like high blood pressure, high cholesterol, sleep apnea, and joint issues such as arthritis in the knees and back that were improved or even eliminated by the initial weight loss.
The graphs below show the typical weight regain after weight loss. Graph 1 below shows the weight loss over 14 weeks while eating three different reduced-calorie diets. No medications were involved. Note the gradual weight gain after 14 weeks despite the same diet program and the very similar weight loss-weight regain patterns, no matter how the weight loss was obtained.
Graph 1: Weight Regain After Non-GLP-1 Weight Loss: NO medications
 graph 1
Graph 2: Weight Regain After Semaglutide Treatment
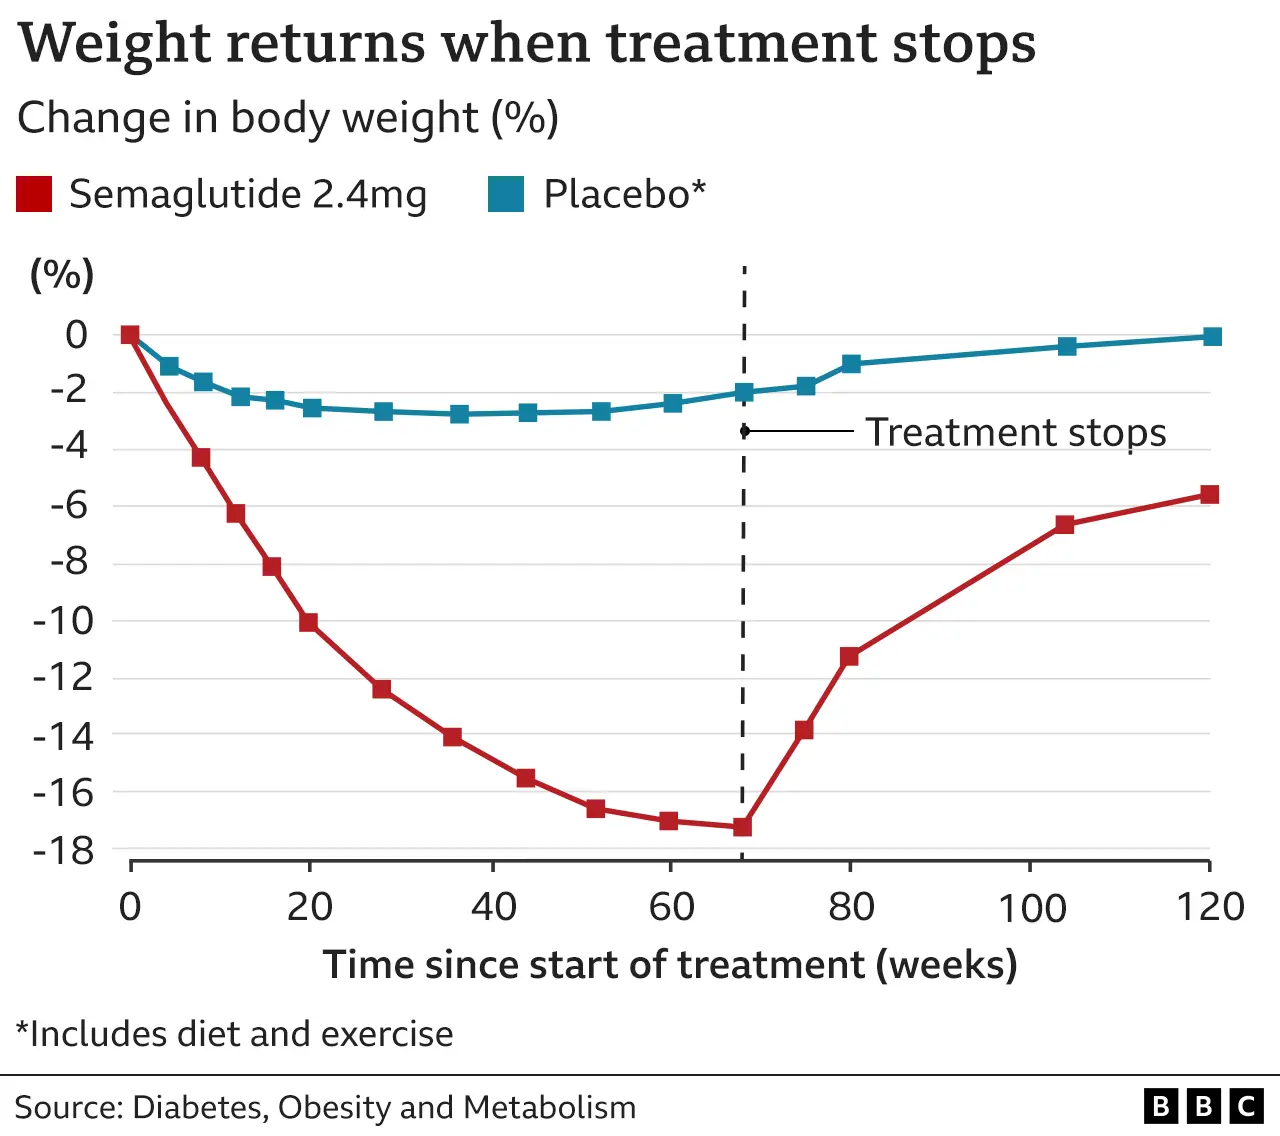
A key determinant of weight regain is the balance between ingested calories and the body’s energy expenditure. Obesity results when small positive energy balances accumulate over a long period. This balance involves both internal and external factors:
Weight Regain after Diet: Due to Hormonal and Metabolic Changes
1. Hormonal changes cause weight regain after weight loss:
Multiple hormone changes after weight loss encourage eating and the regain of the lost weight. The reduction in free Leptin, the increase in Ghrelin (a hormone that promotes eating), and changes in peptide YY (a hormone released from the pancreas that reduces appetite) and GIP (glucose-dependent insulinotropic polypeptide) all converge to promote eating and weight regain. The body interprets even modest weight loss as starvation and makes hormonal adaptations that increase appetite and decrease satiety (fullness) to “help” it regain the lost weight.
Unfortunately, exercise and “healthy eating”are not enough to prevent this almost “normal” response to weight loss. Appetite increases above baseline, resulting in about 45 extra calories per lb of weight lost per day. That is not much, but consider the extra calories after a typical 20-lb weight loss. (45 lb x 20 = 900 extra calories per day!).
2. Slowing of metabolism: ADAPTIVE THERMOGENESIS.
After the weight-loss phase, energy expenditure decreases by about 10-15 calories per day. This contributes to weight gain after the weight-loss phase is completed. More critical are the hormonal factors, which may be four times as much. Graph 3 below shows the reduction in Resting Metabolic Rate (RMR) during the weight-loss phase, with a 125-calorie-per-day drop over the 12-week diet. Similar findings have been reported in the 800-calorie HCG diet.
Graph 3:Reduction in RMR: 
These hormonal and metabolic changes help explain the commonly observed pattern of early rapid weight loss that plateaus after several months, followed by slow but progressive weight regain. Different weight loss plans yield different results, but the overall patterns are similar. As people lose more and more weight, they fight a battle that encourages weight regain.
Often, the dieter is unable to recognize this increase in appetite and food consumption because studies have shown that these overeating signals to the brain are below the level of consciousness. Slowly, food portions get larger, and selections become higher in calories and carbs. Making recognition of this problem even more difficult is the fact that they happen slowly and relentlessly, often over years. However, increasing food noises can be recognized and used to monitor weight regain.
Although the factors causing weight regain are internal to the body, a few external forces also contribute to the battle to maintain weight.
Weight Regain Due to Environmental Factors and Lack of Physical Activity after Weight Loss
1. External factors responsible for weight regain after weight loss: Often, there is a change in the environment with exposure to high-density, high-calorie foods, which are inexpensive and easy to get. This results in mindless eating, grazing, bingeing, and night eating. The result is the consumption of high-calorie, high-carb foods and snacks, often with no easy control. Ultra-processed foods now account for most of the food eaten in the US. Fewer people prepare meals at home, and more food is eaten in restaurants or takeaways.
2. Limit in physical activity: Occupations have become more sedentary, with more driving and less walking. Taken together, changes in food and physical activity tend to drive people to increase their food intake and decrease their physical activity. The net is weight gain, not weight loss.
The idea that exercising for an hour a day and burning 3500 calories over a week, or reducing food intake by 500 calories a day for a week, will result in a 1-pound weight loss is mistaken. Researchers have shown that this calculation is incorrect because it fails to account for the reduced energy expenditure associated with substantial weight loss.
All of these factors act together to produce weight regain after weight loss. This is observed whether weight loss is achieved through simple caloric reduction, increased exercise (graph 1), anti-obesity medications, both older and newer, and even semaglutides such as Ozempic, Wegovy, and Mounjaro (graph 2).
How Once-a-Month GLP-1 Injections for Weight Maintenance Work to Prevent Weight Re-Gain
In his Miami-based medical practice, Dr. Lipman has developed a simple, highly effective strategy that enables patients to maintain their GLP-1 weight-loss results with just one GLP-1 injection per month. On occasion, if the dose is low (5 mg to 7.5 mg of tirzepatide) or the patient reports hunger after 10 days, the injection may need to be administered every other week rather than once a month.
Scripps Clinic in San Diego Reports Similar 2- Week GLP-1 Injection Plan for Weight Loss Maintenance
Successful weight maintenance with reduced dosing of GLP-1’s was first reported by Wu and Cengiz in 2025 in a limited number of patients. The once- or twice-a-month injection program developed in our office is similar to the plan developed at the Scripps Clinic by Dr. Mitch Biermann, who reduced the frequency of GLP-1 medication for 30 patients in the weight-loss maintenance phase to every two weeks, and sometimes longer. The San Diego group found maintenance of body weight and occasional continued weight loss. He noticed no change in AIC or blood pressure with the reduced frequency, similar to the findings with our patients in Miami. Unlike the Scripps Clinic study, which used standard FDA-approved GLP-1 doses, we have been using microdosing to reduce side effects and costs.
A New Approach to Long-Term Weight Control: Why the Once-a-Month GLP-1 Maintenance Injection Works
Having just reached their goal with routine treatment injections, patients have relatively high GLP-1 levels. Many have adopted new foods and eating patterns and may require less appetite suppression to maintain their weight loss. They make better choices when shopping for food and eating in restaurants. They are conscious of what they eat. This continued appetite suppression, reduced cravings, and portion control allow their weight to remain stable. Table 1 shows the protocol.
Table 1: GLP-1 Maintenance Calendar  As the medication’s effect gradually tapers during the last third of the month (from the 20th to the 30th ), appetite begins to return. Patients may notice a mild increase in food intake and cravings, along with more food-related noises. The monthly weight peaks at the end of the month, then returns to the starting weight 2-3 days after the next injection.
Dr. Lipman’s Concept in Weight Maintenance: It’s Not Necessary or Even Desirable to Try to Achieve Zero Weight Gain Each Month
A critical concept in this approach is that the goal is not to maintain a perfectly stable weight every day, but rather to achieve controlled, predictable variation in weight. Small fluctuations of one to two pounds are normal and expected and should not be viewed as a failure. In this process, there is a predictable weight gain at the end of the month, which reverses itself and does not lead to a progressive weight gain as seen when no intervention is attempted post weight loss. This process might be termed cyclical weight maintenance rather than GLP Weight Maintenance. In fact, this pattern reassures patients that the medication cycle is working as intended. Most individuals are not even aware of these fluctuations unless they weigh themselves at the end of the month or in the first few days of the next cycle.
Why has the once-a-month maintenance GLP-1 injection been so successful in Dr. Lipman’s office?
This method is effective because it aligns with both the pharmacologic actions of GLP-1 medications, including resetting brain hunger pathways, reducing food rewards, and improving insulin sensitivity, and patients’ behavioral patterns.
The medication provides a strong initial reset of appetite, followed by a gradual return of hunger that patients learn to anticipate and manage. Over time, patients develop confidence in recognizing their hunger patterns and no longer feel dependent on constant dosing. Additionally, the residual effects of GLP-1 medications continue beyond their peak activity, helping to limit overeating even in the later part of the cycle.
Once Monthly dosing of GLP-1 achieves maintenance
In most cases, the maintenance dose is simply the last effective dose used during the active weight loss phase. There is no need for dose escalation, and many patients can maintain their results on relatively low doses, such as 5 mg of tirzepatide once or twice monthly or an equivalent semaglutide dose. This further contributes to reduced cost and fewer side effects while maintaining weight loss. It appears that much lower doses of GLP-1s are needed for weight maintenance than for weight loss.
What the patient needs to recognize on monthly GLP-1 maintenance
Patients should be clearly advised that a slight increase in hunger near the end of the month is expected and normal. This may be accompanied by a slight increase in food intake and a temporary weight gain of 1 to 2 lbs. This weight gain typically resolves quickly after the next dose is taken. Patients who understand and accept this pattern tend to do very well, whereas those who overreact to minor fluctuations may struggle unnecessarily.
Advantages of Dr. Lipman’s Once-a-Month GLP-1 Injection Program to Maintain Weight Loss
– Marked cost reduction: Fewer doses are required compared to weekly treatments, making the program more affordable. Patients paying $550 or $1000 per month see their costs reduced to $140 or $250 per month. Patients using Dr. Lipman’s Semaglutide compound preparation often pay only $80 per month.
– Improved availability: With fewer doses needed, there is less strain on medication availability. Although injection pens for GLP-1s all cost the same, the lower doses are less popular and much easier to find.
– Better insurance coverage: The reduced frequency of injections may lead to better insurance support for the treatment.
– Reduction in side effects: Monthly administration results in far fewer side effects, improving patient comfort and desire to follow the plan.
– Increased patient compliance: The simplicity of once-a-month injections encourages greater adherence to the treatment plan, leading to better overall outcomes.
Eliminate frequent weigh-ins and overconcern about minor weight gains, and focus on the big picture.
One of the most important aspects of success with this approach is avoiding overreaction to small changes in weight. 
Normal changes in weight during the week are mostly due to minor water weight gains and should be ignored. Instead, consistency with the monthly schedule and trust in the predictable cycle are key. This approach shifts the focus from daily weight anxiety to long-term control and stability.
Monthly GLP-1 maintenance represents a shift in how we think about long-term weight management. Rather than relying on continuous weekly dosing, this approach provides a structured, lower-cost, and more sustainable strategy that empowers patients to maintain their results with confidence. In our Miami practice, Dr. Lipman and his staff have seen this method work successfully in many patients who prefer a simpler, more manageable long-term plan.
———————————–
Note: Once monthly semaglutide or Tirzepatide is an off-label maintenance strategy. These medications are FDA-approved for once-weekly administration, and monthly dosing has not been established by large randomized clinical trials. It should be used only with individualized medical supervision.
Monthly GLP-1 maintenance is promising, physiologically plausible, and supported by early clinical and modeling evidence, but it is currently presented as an individualized off-label strategy rather than an established standard of care.